Journal · 2026-08-31 · 8 min
The periodontium is an architecture
Gum, ligament, and bone are a load-bearing, perfused construction. The periodontal architect is the clinician who names walls, blood, and load before the kit.
Igor Kosmina, DMD · Polyclinic Breyer, Sisak · Consultations for a fee
A tooth is not a post in a painted socket. The periodontium is not a frame around it. Gingiva, cementum, PDL, alveolar bone: four tissues, one construction. They carry bite. They drink. If you treat them as wallpaper, you will plan as if wallpaper were the organ.
I work at Polyclinic Breyer in Sisak, and freelance. I am not applying for a job title. I am naming a habit. The periodontal architect is the person in the room who refuses to open until the construction is named. Walls. Blood. Load. Then the kit.
That order is the whole note. The rest is why we invert it.
Name the members
A three-wall defect is a room. The clot has somewhere to sit. Remaining bone shares the next occlusal cycle. A two-wall crater still has a chance if you tent the missing face. A one-wall slope is hostile. Zero-wall, a flat ridge, a denuded root with no bony peaks: that is a table. I already wrote the chair version: a flat ridge is not a cup. The same graft on a table is a different mechanical object. Morphology is a boundary condition, not a product choice.
The missing pole is the same sentence in soft tissue. Soft tissue is a tent. Interproximal bone is the pole. You cannot pitch the tent above a pole you do not have. Look at the papilla first. Then count the walls. Those are not two specialties. They are two faces of one architecture.
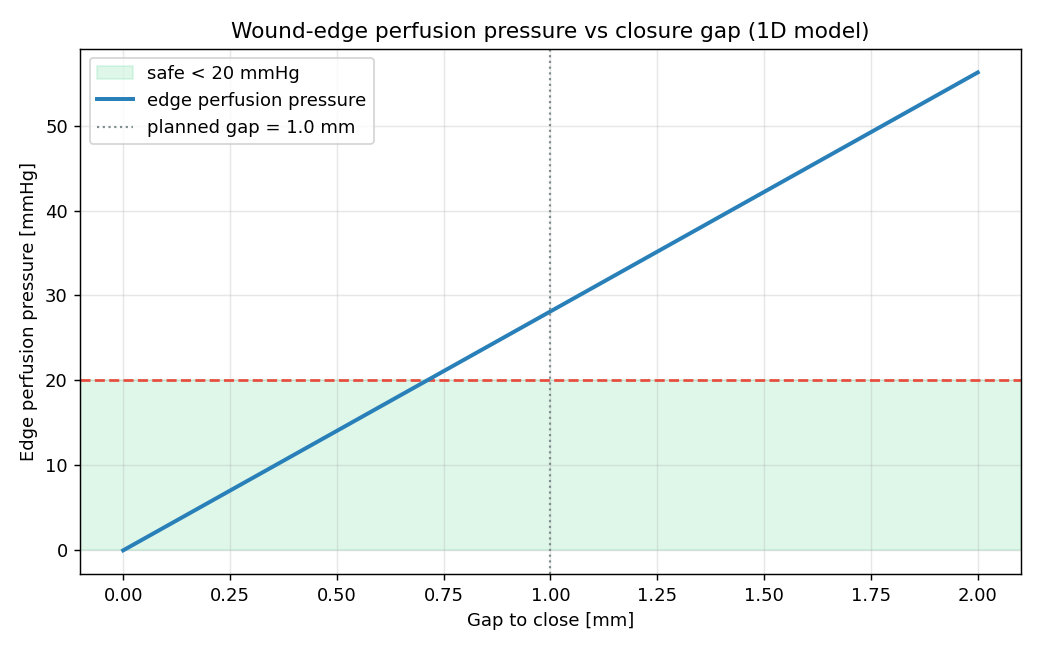
Gap versus edge pressure. Teaching sketch. Not a medical device. Not for diagnosis.
Cementum is the under-discussed interface. Most teaching models glue dentin to PDL and call it done. The clinic does not. Cortical plates and cancellous trabeculae do different jobs. Averaging them into one "bone" modulus is a modelling convenience, not a biological statement. Crestal cortex is where regenerative procedures live and die.
Blood is a member, not a caption
Bone lives near a capillary. Osteocytes are not a powder. A pile on a flat crest is a unilateral healing front: vessels can enter from the bed. They cannot enter from a denuded root. They cannot enter from saliva. Teaching literature puts vascular ingrowth in the neighbourhood of half a millimetre a day. That is a field constant for how far a graft can be asked to wait. It is not a device output. It is not a number from my theatre.
The PDL is a hydro-mechanical tissue. Fiber networks and fluid pressure share the load on short timescales. A dry ligament is a different material. When a papilla goes white under a stitch, the construction just lost a member. Colour is the report.
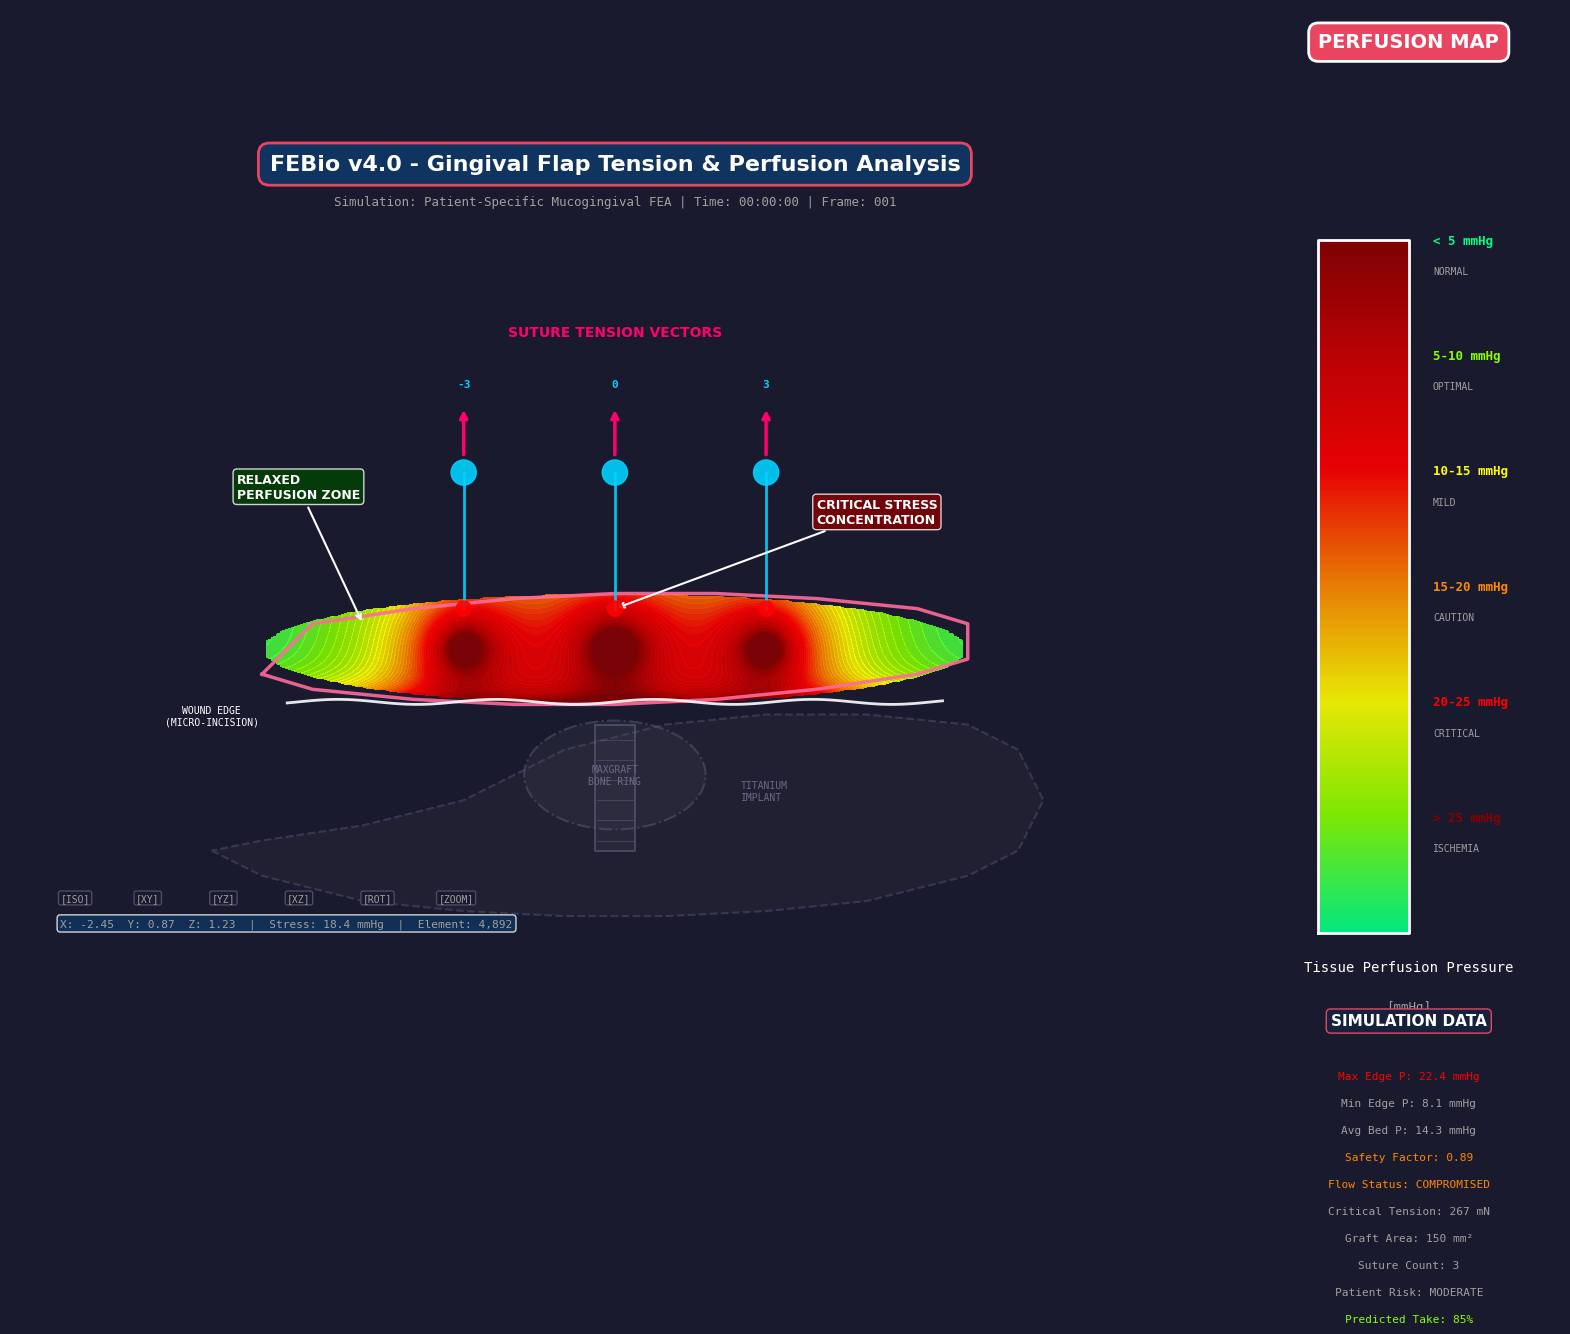
Flap perfusion field. Teaching FEA overlay. Not a medical device. Not for diagnosis.
Urban, the GBR field, the people who actually tent for a living: they already said space without a bed is a haematoma with a product name. PASS is four words: primary closure, angiogenesis, space, stability. I am naming the constraint in public. I am not pasting a CV percentage on top of their cases.
Load is a vector, not a vibe
Occlusal force has a point, a magnitude, and an angle. The PDL is reasonably good at turning axial load into a distributed compressive field. It is less forgiving of a shear component that leverages the crest. Magnitude without direction is an incomplete load. Most failures I see are not "too many newtons." They are newtons arriving at an angle the remaining attachment cannot turn into compression.
A regenerated wall inherits the vector. If the vector is unchanged, biology is being asked to outrun mechanics. That is not a slogan. It is statics in a mouth that will occlude tomorrow morning. The knobs for that sentence are on simulate.
Before the kit
Then you may pick a membrane, a graft, a biologic. Those choices matter. They are not the first choice. A collagen sheet that drapes onto a table is not an architecture. A tunnel that keeps lateral vessels is. A vertical release that spends two nutrient faces for a photograph of the defect is not.
This is teaching. It is not a surgical algorithm. It is not a certified device output. The FEA plates on this site are overlays on a teaching geometry. They are not patient-specific diagnosis. I am not offering a dual-track clinic menu or a percentage from an unpublished series.
The ordered plates start at the lab. Module 01 is the same claim with a figure: four tissues, one load path. If the site is a table, or the pole is missing, say so before you open. The patient in front of you still needs your chart, not a protocol copied off a slide.
The periodontium is an architecture.